
1. When the Immune System Attacks the Kidneys
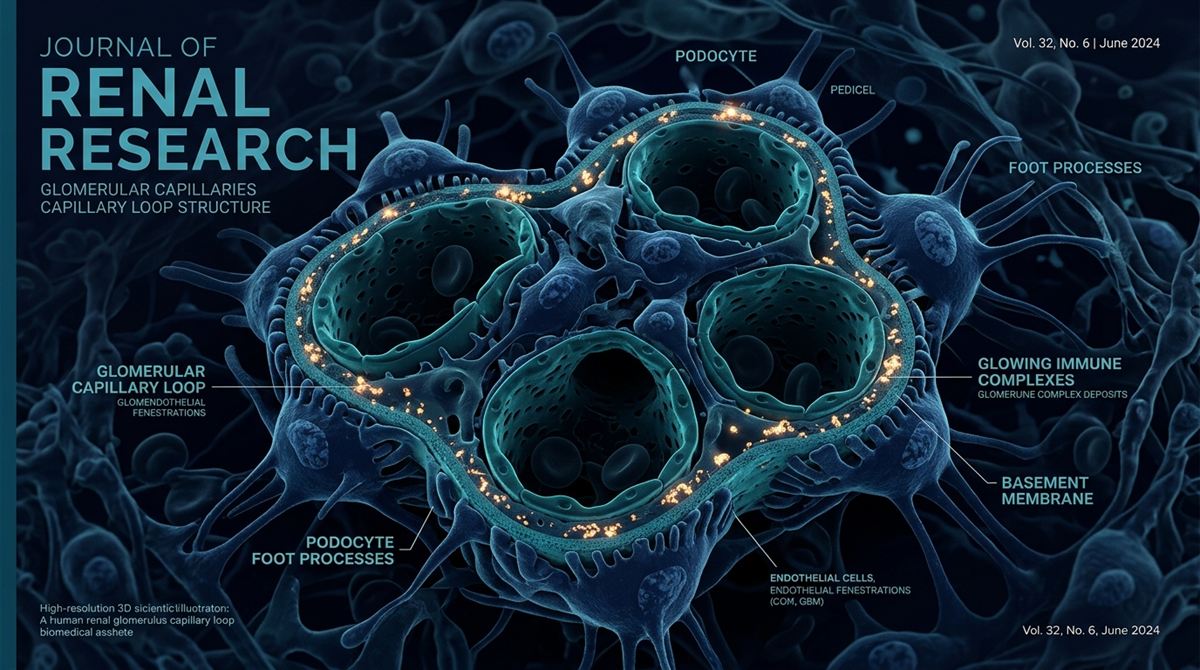
Systemic Lupus Erythematosus (SLE) is a prototypical autoimmune disease in which the body's immune system loses self-tolerance, producing autoantibodies directed against its own cellular nuclei. When these autoimmune complexes circulate in the bloodstream, they frequently lodge in the micro-capillaries of the kidneys, triggering Lupus Nephritis (LN).
Lupus Nephritis is one of the most severe manifestations of SLE. It affects up to 50% of all lupus patients, occurring predominantly in young women between the ages of 15 and 45. Without timely recognition and aggressive nephrological management, lupus nephritis leads to irreversible glomerular scarring and end-stage renal disease within 5 to 10 years.
2. Warning Signs of Renal Involvement in Lupus
Like many glomerular disorders, lupus nephritis can develop silently without physical pain. Every patient diagnosed with SLE must be regularly screened for renal involvement:
- Foamy or Frothy Urine: Indicating significant proteinuria (albumin leaking through damaged glomerular walls).
- Peripheral & Facial Edema: Swelling around the eyelids upon waking, and pitting edema in ankles and feet due to fluid retention.
- Sudden Blood Pressure Spikes: New-onset hypertension in a young female with lupus is a primary hallmark of renal glomerular inflammation.
- Active Urinary Sediment: Microscopic hematuria (red blood cells and cellular casts under urinalysis).
- Rising Serum Creatinine: Signaling acute nephron destruction and declining eGFR.
3. The Golden Role of Renal Biopsy: The 6 Classes
In lupus nephritis, a kidney biopsy is absolutely mandatory. Blood and urine tests cannot determine which cellular compartment of the kidney is inflamed. The International Society of Nephrology / Renal Pathology Society (ISN/RPS) classifies lupus nephritis into six distinct histological classes:
- Class I (Minimal Mesangial): Normal light microscopy; immune deposits seen only on immunofluorescence. Excellent prognosis; no specific renal therapy needed.
- Class II (Mesangial Proliferative): Mild hematuria and low-grade proteinuria; usually responds to low-dose steroids.
- Class III (Focal Proliferative, < 50% glomeruli): Active inflammation, endocapillary proliferation. Requires aggressive induction immunosuppression.
- Class IV (Diffuse Proliferative, > 50% glomeruli): The most severe, aggressive form, often with crescent formation and rapid renal decline. Requires emergency, intensive immunosuppressive therapy!
- Class V (Membranous Nephritis): Subepithelial immune deposits causing massive nephrotic syndrome and high blood clot risks.
- Class VI (Advanced Sclerotic): > 90% globally sclerosed glomeruli representing end-stage chronic scarring; immunosuppression is stopped to avoid toxicity, and preparation for dialysis or transplant begins.
4. The Modern Immunotherapy Revolution
The goal of therapy in Class III, IV, and V lupus nephritis is two-fold: achieve rapid complete renal remission (Induction Phase), followed by maintaining long-term disease quiescence while minimizing steroid side effects (Maintenance Phase).
- Induction Therapy (Months 1–6): High-dose pulsed intravenous Methylprednisolone followed by oral steroids, combined with Mycophenolate Mofetil (MMF) or low-dose intravenous Cyclophosphamide (Euro-Lupus Protocol).
- Targeted Biologic Therapies: Belimumab (a monoclonal antibody that inhibits B-lymphocyte stimulator protein) and Voclosporin (a novel calcineurin inhibitor) have significantly boosted renal complete remission rates when added to standard MMF.
- Hydroxychloroquine (HCQ): Mandatory for all lupus patients unless contraindicated. HCQ reduces renal flare rates by 50% and improves long-term survival.
- Maintenance Therapy (Years 2–5): Low-dose MMF or Azathioprine combined with minimal-dose steroids to prevent disease relapses.
Nephrologist's Clinical Pearl — Dr. Fayaz Ahmad Wani
"A diagnosis of Lupus Nephritis can be emotionally overwhelming for a young woman and her family. But with today's targeted immunosuppressive protocols, the prognosis has been transformed. Over 80% of patients achieve disease remission, preserve their natural kidneys, and can safely plan pregnancies in the future once the disease has been in complete remission for at least 6 to 12 months."
5. Routine Monitoring Protocol for Lupus Patients
Because lupus flares can occur without warning, patients in remission require lifelong monitoring:
- Spot Urine Protein-to-Creatinine Ratio (uPCR) and Serum Creatinine checked every 2 to 3 months.
- Serial blood testing for anti-dsDNA antibody titers and serum Complement levels (C3 and C4). A falling C3/C4 paired with rising anti-dsDNA strongly predicts an impending renal flare before clinical symptoms emerge.
- Strict blood pressure control (target < 120/80 mmHg) using kidney-protective ACE inhibitors or ARBs.
📚 Peer-Reviewed Clinical References & Guidelines
- KDIGO 2024 Clinical Practice Guideline for the Management of Glomerular Diseases: Lupus Nephritis ↗
- American College of Rheumatology (ACR) Guideline for the Screening, Treatment, and Management of Lupus Nephritis ↗
- New England Journal of Medicine (NEJM): Belimumab in Patients with Active Lupus Nephritis (BLISS-LN) ↗
- Fortis Escorts Hospital Amritsar - Department of Nephrology & Autoimmune Renal Disease ↗
Frequently Asked Patient Questions
Can a woman with Lupus Nephritis get pregnant safely?
Yes! Pregnancy is safe and successful provided the lupus nephritis has been in stable, complete remission for at least 6 months, kidney function is stable, and teratogenic drugs (like MMF or ACE inhibitors) are safely switched to pregnancy-compatible medications (like Hydroxychloroquine, Azathioprine, and Tacrolimus) prior to conception.
Why is Hydroxychloroquine (HCQ) recommended for all lupus nephritis patients?
HCQ is a foundational background medication in SLE. It reduces renal flares by 50%, lowers cardiovascular thrombosis risks, preserves kidney function, and significantly reduces long-term mortality.
What happens if Lupus Nephritis leads to kidney failure?
If lupus nephritis progresses to ESRD, patients can safely undergo hemodialysis, peritoneal dialysis, or kidney transplantation. Lupus disease activity typically burns out and becomes quiescent once end-stage renal disease is reached, and lupus recurrence in a transplanted kidney is under 2-3%.
Related Kidney Health Articles
"Medical education empowers patients to make informed, life-saving choices. When we catch kidney decline early, modern nephrology has the tools to protect your kidneys for decades."
— Dr. Fayaz Ahmad Wani
MD (General Medicine), DM Nephrology (Osmania Medical College)
Senior Consultant Nephrologist & Kidney Transplant Specialist
Fortis Escorts Hospital ↗ & Revive Health Clinic, Amritsar